Friday, July 28, 2023

Never Made With mRNA…….

COVID-19 Vaccines and Boosters Were Never Made With mRNA

COVID-19 Vaccines and Boosters Were Never Made With mRNA

(ART-ur/Shutterstock)

Health Viewpoints

For the first time in human history, the gene regulatory program of healthy people has been manipulated on a massive scale.

Despite everything we've been told, RNA-based COVID-19 injections were manufactured with modified RNA—not messenger RNA (mRNA).

Modified RNA (modRNA) poses substantial risks to our health.

These risks come not only from COVID-19 injections and boosters but—unless we speak up now—also from all future RNA-based vaccines.

mRNA and modRNA Are Not the Same

The two—mRNA and modRNA—are completely different.

mRNA occurs naturally, lives in our cells for only a short time, and is relatively fragile. It is a specific type of RNA that carries instructions or "messages" from our genes to help make proteins, the building blocks of our cells. It is constantly produced as part of normal cellular processes. Once mRNA delivers the messages, its work is done, and it is broken down in the body.

When RNA from another source enters our cells—virus RNA, for example—these cells can generate virus proteins.

We have been told that COVID-19 injections are made with mRNA. However, a vaccine using "natural" mRNA would not last long enough to initiate an immune response before being destroyed by our immune system.

To make mRNA useful for routine medicine, scientists had to artificially modify mRNA to increase both its efficiency and lifetime. The result: modRNA.

modRNA has been optimized for long life and maximal translation. While mRNA exhibits a cell-specific expression pattern, modRNA can invade nearly every cell type.

How Did We Get Here?

In 1961, the announcement of the discovery of mRNA occurred "in a climax of scientific excitement." There had been earlier "sightings" of this short-lived but essential RNA intermediary, all leading up to an understanding of how genes made mRNA and its role in the production of proteins.

In a nutshell: mRNA carries genetic instructions from the cell's DNA to ribosomes, which use these instructions to assemble a specific protein.

It wasn't long before scientists experimented with how to use mRNA to help the body heal itself. In 1990, researchers injected natural (unmodified) mRNA into a mouse's skeletal muscle; the mouse produced a protein it would never produce naturally.

Subsequently, scientists observed that transferring natural mRNA was inefficient. Although it worked in principle, it broke down quickly and couldn't be used effectively for treatment purposes.

This observation opened the door to synthetically or artificially modifying mRNA. The original focus of this research was to reprogram and destroy cancer cells—the only aim of modRNA before the COVID-19 pandemic.

modRNA 101

How is RNA modified? Simply put, one of the four compounds in RNA is modified (e.g., the natural nucleoside uridine is modified to make synthetic/artificial methyl-pseudouridine). The modRNA is then:

  • More stable (it lasts longer in the body).
  • Less immunogenic (it evokes reduced stimulation of the innate immune system).
  • More efficient (modRNA produces more protein than the same amount of mRNA).

modRNA is created in a laboratory.

The therapeutic application of modRNA in humans presents challenges and dangers.

Alarmingly, modRNA contains a viral gene sequence. Upon entering a cell, modRNA takes control of the cell machinery and reprograms it to produce a viral protein—for example, spike protein.

Perhaps most astonishing is that, when creating the COVID-19 vaccines and boosters, scientists already knew that targeted delivery of modRNA was impossible. modRNA cannot be targeted to specific cells. As such, it attacks perfectly healthy cells—even beyond natural barriers like the blood-brain barrier.

The continuous production of an artificial viral protein robs the cell of energy, disrupts its metabolism, and leads to the cell no longer being able to perform its vital task for the organism as a whole.

What's worse, with virus proteins generated in them, those cells are subsequently destroyed by our immune system.

Despite these dire shortcomings, Pfizer-BioNTech and Moderna launched a large-scale production of COVID-19 "vaccines" using modRNA.

The Body Responds Differently to Natural Infection Versus modRNA Injection

Spike protein is well known to represent a poison for our body.

In the case of natural infection, our immune system will prevent the virus from infecting our body cells by neutralizing it via specific antibodies, with the possibility of cross-immunity being effective also against virus variants.

With the modRNA injection, our immune system does not have a chance to prevent the lipid nanoparticles from transferring modRNA into our cells—all cells, not just some cells with the appropriate receptor for binding of the virus (as would be the case in natural infection).

The Virus and the Vaccine Are Not the Same

Though some have argued that the body's response to the modRNA vaccine is similar to a response to the actual virus, this is not true.

First, let us look at the natural virus and our body's response to it:

  • The virus RNA is like a blueprint. It contains instructions for all the parts needed (not just for spike protein) to make a new virus.
  • The virus RNA exists within a protein envelope. Our immune system would build various antibodies (not just against spike protein), thus building some degree of cross-immunity to deal with virus variants.
  • The majority of respiratory viruses are prevented from entering our body by the immune system located in the oral and nasal mucosa. The virus does not inject its RNA into blood vessels but binds to a specific receptor on the cell surface and then directly injects RNA into the cell.

It must be emphasized that only specific cells (namely those carrying the appropriate receptor on the cell surface) can be infected.

Our immune system's job is to destroy a cell that has been infected with a virus to prevent replication of the virus and subsequent infection of new cells. Notably, our immune system will stop the process once that battle is won (typically, within a few days).

Next, let us examine the body's response to the modRNA injection ("the vaccine"):

  • The vaccine contains modRNA for only the spike protein; therefore, vaccination provides no cross-immunity.
  • The vaccine-modRNA has no protein envelope but is instead wrapped by a lipid nanoparticle.
  • Lipid nanoparticles will not need receptors to enter a cell. Lipid nanoparticles are built of lipids, as is the cell membrane; therefore, both lipid membranes will simply merge.
  • The immune system generates antibodies to combat antigens, which could include pathogens (viruses, bacteria), foreign particles (fungal spores, allergens), or any substances that provoke a specific immune response. However, the lipid nanoparticles that transport modRNA are devoid of these antigens, enabling them to bypass the specific immune system unnoticed and induce nonspecific inflammation. This dynamic triggers an escalation in the immune system's activity, leading to the production of an increasing quantity of antibodies against the spike protein. Each subsequent booster dose of lipid nanoparticles delivers an escalating quantity of modRNA. This, in turn, prompts an uninterrupted production of new spike proteins.
  • Vaccines are injected into muscle. However, it is nearly impossible to inject directly into a muscle cell (large syringe versus small cell). As muscles are strongly supplied with blood, very often, syringes will violate blood vessels. The normal situation will be that the vaccine will be placed between the muscle cells, the so-called intercellular space. Fluid in the intercellular space will be collected as lymph fluid, finally merging with the blood.
  • The vaccine and booster modRNA will continue to produce spike protein (for weeks or even months, which is entirely different from a natural infection), as our cell machinery (e.g., the enzyme RNase) cannot destroy the artificial modRNA. Researchers have found that some severe cases of COVID-19 were not due to the presence of the virus but to a dysregulation of the immune system (called a "cytokine storm").

Research Reveals modRNA's Poor Safety Profile

Early preclinical studies generated optimism about the advantages of RNA-based injections. However, the ability to induce an immune response was less effective in humans than anticipated based on animal experiments.

A 2018 review published in Nature reported that "recent human trials have demonstrated moderate and in rare cases severe injection site or systemic reactions for different mRNA platforms."

Hence, the focus shifted to modRNA.

Injected modRNA can result in thrombosis followed by stroke, myocardial infarction, or pulmonary embolism and can promote the formation of blood clots inside blood vessels.

Studying the open-access databases—including those in the United States, Europe, and the UK—on COVID-19 vaccine adverse effects, one can see that these risks have become real-life side effects for people who received the COVID-19 injections.

Just Released: Previously Confidential Report on COVID-19-Related Fatalities

In June 2023, in response to a Freedom of Information Act request, some of these adverse effects were made public when previously confidential reports by BioNTech to the European Medicines Agency (EMA) were released. The reports included data collected during a six-month period from December 2021 to June 2022 and cumulative data beginning December 2020 (pdf).

The data revealed 3,280 fatalities among a group of 508,351 individuals receiving the vaccine during a combined period that included clinical trials and postmarketing. These deaths, and tens of thousands of serious adverse events, happened during a period when the vaccine makers insisted the modRNA-based injections were safe.
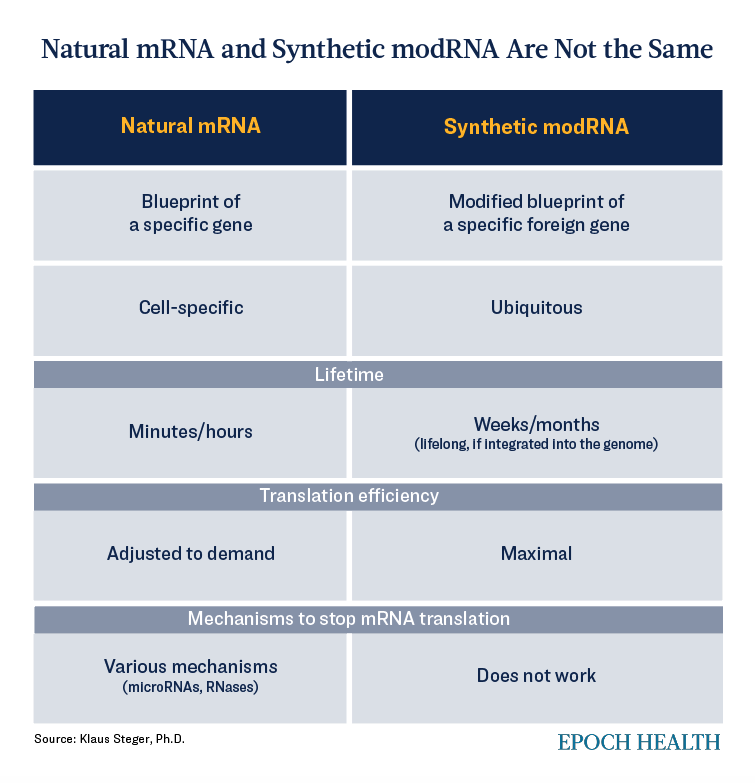
Natural mRNA and synthetic modRNA are not the same. (The Epoch Times)

It is nonsensical that any cell in our body would be programmed to produce as much of a viral protein as possible for as long as possible. This is highly contrary to natural viral infection and will result in hyperactivation of the immune system.

Forcing perfectly healthy people to take a gene-based modRNA injection—sold as a vaccine—is both unethical and dangerous.

Views expressed in this article are the opinions of the author and do not necessarily reflect the views of The Epoch Times. Epoch Health welcomes professional discussion and friendly debate. To submit an opinion piece, please follow these guidelines and submit through our form here.




~A.

Thursday, July 27, 2023

Still Excommunicated ???? What happened to these Cadets???


After Coast Guard Academy 'Excommunicated' Cadets For Refusing Vaccine, Pleas For Reinstatement Go Unanswered

Donald Trump Delivers Commencement Address At U.S. Coast Guard Academy

(Photo by Drew Angerer/Getty Images)

  • The Coast Guard Academy has not reinstated seven Coast Guard cadets discharged for refusing the COVID-19 vaccine after the academy denied religious exemption requests, representatives of the cadets told the Daily Caller News Foundation.
  • The cadets hoped a new law nixing the military's COVID-19 vaccine mandate would allow them to re-join.
  • "They are the only cadets that are getting screwed," retired Coast Guard Vice Adm. William Dean Lee told the DCNF.

Seven Coast Guard cadets booted in September after commanders denied their vaccine exemption appeals were not reinstated after a last ditch effort to allow them to start the new semester, which began Wednesday, representatives of the cadets told the Daily Caller News Foundation.

The cadets hoped that law overturning the Department of Defense (DOD) COVID-19 vaccine mandate would persuade the Academy to permit the cadets, already behind by one semester, to re-join with their cohort, one of the cadets involved and advocates for the group told the DCNF. Among the military schools, the Coast Guard Academy, which operates under the Department of Homeland Security (DHS) in peacetime, is the only one to have officially dismissed unvaccinated cadets, the advocates said.

"I sent a letter to the Coast Guard Academy superintendent asking him to use his administrative powers to have us go back in since the [National Defense Authorization Act] was signed by the president and the mandate should be lifted soon," Sophia Galdamez, one of the seven discharged, told the DCNF. (RELATED: Coast Guard Illegally Denied Hundreds Of Vaccine Exemptions, Attorneys Say)

"However, all he responded with is that it's out of his control, and you don't have authority over that decision. And for me and my family to have a happy holidays," she added.

Although operating under DHS authority, the Coast Guard went along with the mandate after Defense Secretary Lloyd Austin announced it in August 2021 as the FDA officially approved the first COVID-19 vaccines for use. Congress' defense bill for 2023, signed into law on Dec. 23, overturned the service-wide vaccine mandate.

Despite being a semester behind the other cadets in their cohort, the seven could still achieve their commissions if the Coast Guard allowed them to rejoin, retired Coast Guard Vice Adm. William Dean Lee, who, along with retired Rear Adm. Peter J. Brown, is lobbying to have the cadets reinstated, told the DCNF. Cadet processing began Wednesday, while classes are slated to begin on Jan. 9.

After initially refusing the vaccine on the grounds of religious belief in the fall of 2021, "I was immediately treated differently than all my other classmates that were vaccinated," Galdamez told the DCNF. "I was bullied by my command and administrators, faculty at the academy."

Administrators confined her behind a plexiglass barrier at the back of the classroom, she told the DCNF. One teacher pulled her aside to commend her performance as a student, but said her unvaccinated status would impede academic progress, Galdamez said.

She and her fellow unvaccinated cadets submitted requests for religious exemptions, which authorities are required to review on an individual basis.

Citing the government's "compelling interest in mission accomplishment," the force's time sensitive role in emergency response and high rate of interaction with the general public, Coast Guard adjudicator Capt. Eugenio S. Anzano shot down Galdamez's exemption request in a letter, dated March 4, 2022, that was shared with the DCNF.

"I do not question the sincerity of your religious belief or whether vaccine requirements substantially burden your religious practice. The Coast Guard reserves the opportunity to make these determinations, but I do not need to address them here to resolve your request," Anzano wrote.

When the Coast Guard denied Galdamez's request, she appealed, but the answer remained firm. The Coast Guard struck down Galdamez' appeal on May 2, according to a copy of the response letter shared with the DCNF.

Days after reporting to campus for the fall semester on Aug. 15, the cadets were called into the office and told they had 24 hours to pack and leave campus, Galdamez said, a statement echoed by Michael Rose, a pro-bono legal counsel for several of the cadets, according to The Day newspaper. Two of the cadets did not have homes to which to return.

The cadets were formally discharged on Sept. 23, according to Stand Together Against Racism and Radicalism in the Services, where Rose serves as general counsel.

"I sent letters to the academy, senators have written letters on [sic] the cadets' behalf. And so far we have heard nothing regarding our reinstatement or if I'd be able to finish my degree and commissions," Galdamez told the DCNF Wednesday.

Academy superintendent Rear Adm. William Kelley acknowledged receipt of Galdamez' letter and wished her a "good holiday season" but did not indicate future action in an email dated Dec. 22 that was shared with the DCNF.

Republican Sen. Lindsey Graham of South Carolina wrote to Coast Guard Commandant Adm. Linda Fagan pressing for the servicemembers' reinstatement, according to a Dec. 22 letter the senator's office shared with the DCNF.

The US Coast Guard ship Sycamore arrives in New York Harbor for Fleet Week on May 25, 2022.
The US Coast Guard ship Sycamore arrives in New York Harbor for Fleet Week on May 25, 2022. (Photo by ANGELA WEISS/AFP via Getty Images)

Galdamez is one of thousands of servicemembers who remain in limbo as the DOD develops new guidance on COVID-19 vaccination, while lawsuits challenging the legality of the mandate and whether military leaders appropriately considered exemption requests continue to make their way through court.

The Air Force and Navy and Marine Corps have been placed under an temporary injunction against discharging unvaccinated troops, while the Army has paused separations.

"They are the only cadets that are getting screwed," Lee told the DCNF.

The National Defense Authorization Act gave DOD a 30 day period to develop new COVID-19 guidance but stopped short of calling for reinstatement or restitution to the roughly 8,400 already discharged for refusing to receive the vaccine.

"The Coast Guard, in coordination with the Department of Defense, is evaluating policies with respect to previously separated members, including cadets," a spokesperson for the Coast Guard told the DCNF.

"I think it's important to let the service members back in, and for the service members to accept going back in, because this mandate and then the subsequent denial and basically excommunication of all these service members was getting rid of a good group of people … enlisted and officers alike that display true leadership qualities that are needed in our military at the moment," Galdamez said to the DCNF.

The Coast Guard Academy did not return a phone call from the DCNF.

All content created by the Daily Caller News Foundation, an independent and nonpartisan newswire service, is available without charge to any legitimate news publisher that can provide a large audience. All republished articles must include our logo, our reporter's byline and their DCNF affiliation. For any questions about our guidelines or partnering with us, please contact licensing@dailycallernewsfoundation.org.


Institute for Nearly Genuine Research: Shopper's Guide to 22 Worthless Drugs


http://www.bonkersinstitute.org/simpleside.html


Click on drug name to view complete list of side effects (aka adverse events)
sorted alphabetically for your shopping convenience.

1,182 Abilify side effects
  819 Adderall side effects
1,658 Celexa side effects
1,989 Cymbalta side effects
1,994 Depakote side effects
2,356 Effexor side effects
1,366 Geodon side effects
1,100 Klonopin side effects
2,233 Lamictal side effects
1,886 Lexapro side effects
2,672 Neurontin side effects
2,497 Paxil side effects
1,817 Prozac side effects
1,935 Risperdal side effects
1,195 Ritalin & Concerta effects
1,656 Seroquel side effects
2,025 Strattera side effects
2,270 Tegretol side effects
1,773 Wellbutrin side effects
1,356 Xanax side effects
2,194 Zoloft side effects
2,962 Zyprexa side effects


~A.

‘Chemical Imbalance’ “”Theory of Depression “”

'Chemical Imbalance' Theory of Depression Hugely Profitable—and It's Not Even True

'Chemical Imbalance' Theory of Depression Hugely Profitable—and It's Not Even True(old news)

Worldwide sales of SSRIs have been estimated to soar as high as $18.29 billion by 2027. (Maxx-Studio/Shutterstock)

"Lexapro appears to relieve the symptoms of depression and anxiety by increasing serotonin," says an ad on the Bonkers Institute, a website that archives drug ads and also satirizes pharma claims and shaky science.

"Zoloft works to correct a chemical imbalance in the brain which may be related to symptoms of depression," another ad says.

"Paxil CR blocks serotonin from being reabsorbed back into the sending nerve cell. This process increases the availability of serotonin to the receiving nerve cell and may help message [depression] transmission return to normal," a third ad says.

As many Epoch Times readers may have heard, the serotonin "chemical imbalance" theory of depression was recently put to rest by a group of University College London (UCL) scientists in the journal Molecular Psychiatry. After reviewing decades of research, there's no evidence that serotonin levels or serotonin activity are responsible for depression, they wrote. In other words, the theory that was the basis for selective serotonin reuptake inhibitor (SSRI) antidepressants and their tremendously profitable franchise was false.

While the theory has been questioned by scientists for decades, the Molecular Psychiatry research seems to be the final nail in the coffin for the theory—a technical knockout.

"The popularity of the 'chemical imbalance' theory of depression has coincided with a huge increase in the use of antidepressants," said the article's lead author, Joanna Moncrieff, a professor of psychiatry at UCL. "Prescriptions for antidepressants have risen dramatically since the 1990s.

"Thousands of people suffer from side effects of antidepressants, including the severe withdrawal effects that can occur when people try to stop them, yet prescription rates continue to rise.

"We believe this situation has been driven partly by the false belief that depression is due to a chemical imbalance. It is high time to inform the public that this belief is not grounded in science."

A Powerful Drug Franchise

It's hard to overestimate the medical, financial, and sociological consequences of the chemical imbalance theory, which propelled the 1987 FDA approval of the SSRI antidepressant Prozac and which is still followed to this day. Several years ago, Harvard Health Publishing estimated that about 1 in 4 American women in their 40s and 50s were taking antidepressants.

Thanks to direct-to-consumer marketing (or "mongering," as some say) about depression, people with life problems or occasional bad moods absorbed the chemical imbalance messaging, diagnosed themselves with depression, and presented themselves to doctors' offices.

Family, job, health, money, or housing problems were no longer a reason for feeling down or defeated, suggested aggressive SSRI advertising campaigns; if you were depressed, you had a chemical imbalance—regardless of whatever else may have accounted for your depression (such as the loss of meaning and social connection often observed in modern society).

Whereas the antidepressants that preceded SSRIs, some called monoamine oxidase inhibitors, were connected to neurotransmitters in the brain such as serotonin, dopamine, and norepinephrine, SSRIs reduced the chemistry to a simple problem-solution equation, which the public readily bought. Thanks to the new chemical imbalance of serotonin theory of depression, drugmakers had a formidable new franchise; doctors, a ready-made, patient-pleasing tool; the media, reliable new advertisers; and Wall Street, hot new stocks—all almost overnight. Worldwide sales of SSRIs have been estimated to soar as high as $18.29 billion by 2027.

Your Health Matters

Response From Mainstream Medicine

Psychiatrists and the American Psychiatric Association (APA), which is highly funded by drugmakers—70 percent of authors of the APA's Diagnostic and Statistical Manual of Mental Disorders Fifth Edition were drugmaker funded, as reported by ABC news—were among the first to push back against the Molecular Psychiatry article. Chief among protestations were "we never promoted the 'chemical imbalance' theory"—no, you let drug makers do that, cynics might say—and "no one really understands why or how antidepressants work."

The "third rail" for drugmaker-funded practitioners is the suggestion that mental illness may not be from physical conditions at all. As Mark Horowitz, co-author of the Molecular Psychiatry article, put it, "One interesting aspect in the studies we examined was how strong an effect adverse life events played in depression, suggesting low mood is a response to people's lives and cannot be boiled down to a simple chemical equation."

If depression comes from stress, trauma, grief, loneliness, and social conditions such as poverty, as Horowitz suggests, it wouldn't be amenable to medication treatment. Worse, if it weren't a permanent chemical imbalance as the serotonin theory of depression implies, it wouldn't turn into lifelong medication prescriptions, which drugmakers seek and treasure the most.

"Although viewing depression as a biological disorder may seem like it would reduce stigma, in fact, research has shown the opposite, and also that people who believe their own depression is due to a chemical imbalance are more pessimistic about their chances of recovery," Moncrieff said.

Psychiatrist Peter Breggin, who has been called the Conscience of Psychiatry, elaborated on this idea to The Epoch Times:

"Since the ancient Greeks, physicians have wanted to believe the mental and emotional distress must have biological origins. That allowed them to include 'mental diseases' within their specialty.

"With the development of massive drug company involvement in routine psychiatric practice during the advent of the antipsychotic drugs in 1954, drug companies also began pushing the biochemical and biological basis of human experiences such as anxiety, depression, manic-depression (now bipolar-disorder), and schizophrenia.

"Then, in the late 1980s, in anticipation of the approval of Prozac for depression by the FDA, Eli Lilly and Company conducted an international advertising campaign claiming that depression is caused by a biochemical imbalance in serotonin. It was apparent from the start that this was pure fantasy.

"In my books and scientific articles as far back as 1983, I pointed out the continuing truth that there are no known biochemical imbalances in the brains of mental patients until they are put there by the neurotoxic effects of all psychiatric drugs.

"Now, a review article by British psychiatrist Johanna Moncrieff has reconfirmed that research fails to show any connection between depression and abnormalities in serotonin metabolism in the brain. No so-called 'mental illnesses' are known to be genetic or biochemical in origin—it's all medical and pharmaceutical company hype."

Don't Stop SSRIs Abruptly, Warn Both Sides

Whether they believe SSRIs are specious and over-prescribed or valuable treatments, clinicians warn patients not to stop the drugs abruptly.

In 2018, The New York Times exposed that SSRI antidepressants can be difficult to quit and downright addictive (though drugmakers prefer to call the addiction effects a "discontinuation syndrome"). Some patients say they weren't warned by their doctors that they may be indefinitely parked on the drugs because of the side effects such as dizziness, nausea, headache, and brain zaps that they experience when trying to stop the drugs, the newspaper reported.

Brian, a 29-year-old Chicagoan who asked not to give his last name, said that he has remained on an SSRI antidepressant for years despite his wish to quit.

"Every time I try to stop, I get something that feels like an electrical current in my head, and I can't do it," he said.

The NY Times article drew a huge backlash from psychiatrists. "By amplifying the social media echo chamber, the article creates the unfortunate impression that most patients are forced to continue antidepressants out of fear of withdrawal rather than out of prevention of recurrence," read a letter to the editor signed by a group of 39 psychiatrists, who termed depression as "chronic" and "undertreated." At least 35 of the letter signers were affiliated with Columbia Universityʼs College of Physicians and Surgeons, an institution that received a $250 million gift from former Merck CEO Roy Vagelos and his wife, Diana, in 2017.

Since their original marketing, SSRI antidepressants are also now known to increase bone loss and fracture risk, as well as the risk of the dreaded intestinal condition of Clostridium difficile.

Then, Why Do SSRIs Work?

It's generally agreed that SSRI antidepressants sometimes work, though not impressively, and not for all patients. But why? According to a follow-up paper by Moncrieff and Horowitz, "Any drug that changes normal brain activity is likely to have some impact on mood, and … by virtue of changing brain chemistry, antidepressants also produce changes to normal mental activity and experiences."

Antidepressants also cause numbing of the moods, the researchers say—"including not just sadness and anxiety but welcome emotions like happiness and joy"—which can reduce depression scores, making the drugs appear to be effective.

A paper in the Springer journal Inflammopharmacology suggests a possible SSRI mechanism could be decreasing "neuroinflammation [in the brain] through multiple mechanisms including the reduction of blood or tissue cytokines or regulating complex inflammatory pathways."

Whatever the explanation, it remains true that other methods to treat depression, including exercise and cognitive behavioral therapy, have proven efficacy with additional benefits and no side effects.

A Final Irony

Even as the premise through which millions of Americans were put on psychoactive drugs has been demolished, raising questions about the interface between medical care and misleading drug marketing, some news outlets have sought to politicize the contretemps.

Many media outlets went on the attack after Fox News host Tucker Carlson said: "First, we were told that SSRIs would save lives. Now, we learn they don't actually work as intended. In fact, the whole idea behind the drug was completely wrong. And yet—and here is the best part—people are ignoring this news, and the drugs are still being prescribed."

Rolling Stone magazine published a hit piece portraying Moncrieff as a conspiracy nut with a history of criticizing the over-medication of mental conditions and attributing some mass shootings to psychoactive drugs. The article, "Who Is the Psychiatrist Behind the Antidepressant Study Taking Over Right-Wing Media?", reveals the 180-degree turn that progressive outlets have taken toward drugmakers since COVID-19—forgiving and forgetting original distrust of corporatism, capitalism, monopolies, and the drugmaker-caused opioid scourge—in order to be able to demonize rivals.

Meanwhile, millions on SSRI antidepressants now face the prospect of quitting.


~A.

Monday, July 17, 2023

Saturday, July 08, 2023

The ‘Threads’ App is FILLED With Deceptive Dark Design Patterns – We Spotted More Than TEN - Yanko Design

The 'Threads' App is FILLED With Deceptive Dark Design Patterns – We Spotted More Than TEN - Yanko Design

The 'Threads' App is FILLED With Deceptive Dark Design Patterns – We Spotted More Than TEN

Aside from probably the launch of ChatGPT, I can't ever recall a recent time in which the internet was THIS excited. While I personally believed that Zuckerberg's new Threads app was doomed to be a hit and miss, it seems like I was dead wrong – the app saw more than 10 million users sign up in just 1.5 hours, with the number climbing up to 75 million as per a recent announcement from Zuckerberg. The reason? FOMO, along with the fact that the Threads app was designed to be incredibly intuitive. You didn't need to make an account – if you were on Instagram, the account was already made for you. A simple click would import all your followers, your profile settings, and profile-picture and bio. However, veiled underneath that ease and convenience were a few patterns that designers and tech nerds were all too familiar with. These patterns, referred to as Dark Design Patterns, are known to manipulate and influence a user into doing something against their will.

As a user, you've probably encountered a whole bunch of dark design patterns in your life. If you've used the Uber app, you're familiar with how notorious it is to cancel a ride while the app is searching for one. The 'Cancel Ride' button is greyed out, but the 'Continue Searching' is black and highly visible. Hit the Cancel button and Uber asks you at least twice if you're sure you want to cancel. Amazon does the same thing with its Prime subscribers. Try canceling your Prime subscription and chances are you'll just give up because Amazon's made it so incredibly hard to cancel an active Prime membership.

The Threads app almost immediately displayed a whole bunch of dark patterns with its user interface. We spotted at least 11 of them, and we're sure there are a lot more to come. Here are some highly evident dark tricks the Threads app is using to ensure you stay on the platform as long as you possibly can… and supply Meta with even more data than before.

1. In order to first make your Threads account, you need to log in through Instagram. The Threads app doesn't let you create an account WITHOUT having an Instagram account. It does so to make the transition for Instagram users incredibly easy… but in doing so, it also ensures that people NEED to have both Instagram and Threads accounts active at all times. There's no Threads without Instagram, so if you gave up your IG for any particular reason, you're in a tough spot.

2. While onboarding users was designed to be easy, the Threads app does something notorious to ensure users don't leave too. If at any point in time you feel the need to 'delete' your Threads app, it means you'll have to delete your Instagram too. Sounds bizarre, right?! Well, the settings panel in the Threads app mentions that "deleting your account apply to both Threads and Instagram", taking the ability to selectively delete your accounts right out of your hands.

3. As a form of consolation, Threads does allow you to 'deactivate' your account. This takes your Threads profile offline… but the data still exists on Meta's servers, and it still remains tied to your IG at all times to help Meta build that dataset on you.

4. The reason why joining Threads was so easy was because your account was already created for you in advance. Prior to the launch, a Threads section on your Instagram page would give you a QR code and tell you that your IG handle was already reserved for you on Threads. It's easy because the app is literally being handed to you on a silver platter with your username already pre-selected. This dark pattern becomes even darker because if your IG accidentally gets hacked, the hacker gets your Threads account with it, with little to no effort.

5. However, if you've somehow resisted joining Threads, don't worry because Instagram makes it incredibly easy for others to share Threads content on the IG app – as a post, a story, or even a DM. This means that there's really no escaping Threads content even if you made the conscious decision to NOT sign up for it. The fact that it's so easy to share your Threads on Instagram just makes it grow faster, and in doing so, trap more users easily (Threads has already reported 95 million posts on the app). Don't think it's a dark pattern? Well, think of it as being incredibly anti-competitive to all of Thread's newer rivals like Mastodon or Blue Sky.

6. The Threads app conveniently copies all your profile settings from Instagram, but requires you to manually set your notification settings all over again. Moreover, just like Facebook and Instagram are often filled with bogus notifications, the Threads app will send you a ping every time someone you know joins Threads… a classic dark pattern to have you constantly checking the app every few minutes.

7. The Threads app doesn't just copy profile settings, it basically mirrors all your IG data, providing Meta with yet another avenue for advertising. Sure, the Threads app doesn't have ads or sponsored content, but don't be surprised if you get ads on Instagram for stuff you speak about in Threads.

8. Perhaps one of the most malicious dark patterns lies in how much data the app collects on you. Even though Threads is essentially just a microblogging platform, the app has access to your health data, financial data, and even your location. In fact, ex-CEO of Twitter Jack Dorsey shared a snippet of the amount of data the app collects on you and it's shocking. If you're in the EU, you probably don't have access to Threads for this exact reason, because the European Union has some incredibly strict laws on data gathering.

9. And even though Threads makes it very easy to share stuff to Instagram, your IG followers can't view your thread unless they install the app and make their account too. The most they can see is a snippet, which lures them into signing up.

10. The above is reinforced by the fact that Threads doesn't have a desktop website either. Even though its competitor Twitter does, and even though Instagram does too, Threads can ONLY be accessed by installing an app, and logging in. That's how Meta coerces you into installing an app that you then can't remove… and an app that then constantly gathers data on you.

11. This one verges more on speculation at this point, but Threads rather visibly lacks DMs. It's true that Meta is building out the feature as of now, but there's a high chance those DMs will also be connected to your Instagram DMs. Famously a few years ago, Meta merged IG DMs with Messenger in order to facilitate cross-platform messaging (and in order to revive Messenger, which saw a slow but steady decline). While there's no concrete evidence to back this, it'll be interesting to see if Meta chooses to centralize Threads and Instagram DMs into one channel, creating yet another dark pattern. All we can do right now is wait and watch…


~A.

Friday, July 07, 2023

Wednesday, July 05, 2023

Saturday, June 24, 2023

Monday, June 19, 2023

Timeline of End Dates for Key Health-Related Flexibilities Provided Through COVID-19 Emergency Declarations, Legislation, and Administrative Actions | KFF

Timeline of End Dates for Key Health-Related Flexibilities Provided Through COVID-19 Emergency Declarations, Legislation, and Administrative Actions | KFF

Timeline of End Dates for Key Health-Related Flexibilities Provided Through COVID-19 Emergency Declarations, Legislation, and Administrative Actions

In response to the unprecedented nature of COVID-19, the federal government declared numerous types of emergencies, Congress enacted several pieces of legislation, and various executive actions were taken and waivers issued, which, collectively, established time-limited flexibilities and provisions designed to protect individuals and the health system during the pandemic. The effective end dates of many, though not all, of these flexibilities and provisions are tied to the public health emergency (PHE) declaration made pursuant to Section 319 of the Public Health Service Act, first declared in January of 2020.  Others are linked to the public health emergency declaration made under Section 564 of the Federal Food, Drug and Cosmetic (FD&C) Act; the declaration made under the Public Readiness and Emergency Preparedness (PREP) Act; and emergency and major disaster declarations made under the Stafford Act. In some cases, subsequent legislation has either delinked provisions from these declarations or otherwise changed their duration.

The Biden Administration recently announced that it will end the PHE on May 11, 2023 and FEMA has announced that the emergency incident period under the Stafford Act will also end on that date. Other related emergency declarations or provisions have already ended or are ending soon. The following table (Table 1) provides a timeline identifying key health-related flexibilities and provisions specified by these various measures, the specific measure that determines their end date, and their end date (an end date for the Section 564 declaration has not yet been announced).

In addition to the end of the flexibilities detailed in Table 1 below, there are also expectations that the federal supply of COVID-19 vaccines could be depleted or need to be replaced by an updated booster dose sometime this year and, similarly, the federal supply of COVID-19 treatments will also be depleted. At a result, COVID-19 vaccines and treatments are transitioning to the commercial market. Importantly, this change is not tied to the end of the public health emergency.


~A.

State Policy Choices Are Likely to Affect the Extent of Medicaid Enrollment Declines During the Unwinding Period | KFF

State Policy Choices Are Likely to Affect the Extent of Medicaid Enrollment Declines During the Unwinding Period | KFF

State Policy Choices Are Likely to Affect the Extent of Medicaid Enrollment Declines During the Unwinding Period

NOTE: This analysis, originally published on April 26, 2023, was updated on May 9, 2023 to include newer state data.

Starting on April 1, 2023, all states have begun the process of unwinding the Medicaid continuous enrollment provision. Adopted in March 2020, the continuous enrollment provision has protected coverage for millions enrolled in Medicaid during the past three years. Because states were prohibited from disenrolling people from Medicaid in exchange for enhanced federal funding, enrollment in the program has grown by an estimated 23 million to reach 95 million as of the end of March 2023. Now that continuous enrollment has ended, over the next year (and more quickly in some states), states will redetermine eligibility for everyone enrolled in Medicaid and will disenroll those who are no longer eligible, as well as those who remain eligible but who face barriers to completing the renewal process. Millions of people are expected to lose Medicaid coverage nationally.

The unwinding of the continuous enrollment provision will play out differently across the states based on policy choices states have made and variation in their administrative infrastructures. Some states have adopted multiple policies that are more likely to promote continued coverage among those who remain eligible. Others have adopted fewer of these policies, which will likely lead to a larger number of people losing Medicaid coverage, including some who remain eligible. Additionally, some states have automated eligibility systems that can more easily and accurately process renewals, reducing the number of renewals staff will have to complete manually. Having some way to order states based on their adoption of polices and strategies to promote continued coverage, as well as the capacity of their systems to process the expected volume of renewals, can be helpful for identifying where larger decreases in Medicaid enrollment are more or less likely.

Key Unwinding Metrics

Using data from a survey of state Medicaid eligibility, enrollment, and renewal policies conducted by KFF and the Georgetown University Center for Children and Families (CCF) earlier this year, we have identified 9 key metrics that will support continued Medicaid coverage during the unwinding for those who remain eligible. They include a mix of policy choices and measures of systems capacity and are grouped into three categories: renewal policies in place during the unwinding, systems for processing of renewals, and eligibility policies that promote continued coverage. The metrics include:

Renewal Policies

  • State will take 12-14 months to complete all renewals
  • State follows up on returned mail
  • State follows up with enrollees who have not responded to a renewal request before terminating coverage

System Capacity Measures

  • Processing of renewals is mostly automated
  • 50% or more of renewals are completed on an ex parte basis
  • State has taken steps to improve ex parte renewal rates

Eligibility Policies

  • State has adopted the Medicaid expansion
  • State has adopted 12-month postpartum coverage
  • State has adopted 12-month continuous eligibility for all children in Medicaid and CHIP

Importantly, the data included in this analysis reflect policies and procedures in place as of January 2023; it is possible, likely even, that states have updated some policies in response to guidance from the Centers for Medicare and Medicaid Services (CMS) or mitigation plans developed in coordination with CMS. In addition, some states indicated they were not processing ex parte renewals as of January 2023 and we cannot distinguish between states that paused ex parte renewals while the continuous enrollment provision was in place and those that may not have the system capacity to process ex parte renewals. Ex parte renewals involve automatically renewing coverage based on available data sources. Finally, some states did not provide data for one metric included in this analysis. States with missing data are noted in the figure below.

How Do States Compare Across Unwinding Metrics

Overall, states fall along a spectrum on meeting the metrics. Nine states meet eight or more of the metrics for promoting continuity of coverage, including one state, Colorado, that meets all nine metrics. At the other end of the scale, six states meet four or fewer of the measures (Figure 1). The majority of states fall somewhere in the middle, meeting all of the metrics in some categories but not others. More states (29) meet all of the metrics related to adopting renewal policies that promote continued coverage during the unwinding than meet the standards for metrics in the other two categories (7 states for system capacity and 14 states for eligibility policies).

Most states do not have fully automated systems that are capable of completing a majority of renewals using ex parte processes. A total of 42 states do not meet all three of the metrics that measure the capacity of state systems to process ex parte renewals. The total includes 14 states that reported having mostly manual systems for processing renewals or reported processing less than 25% of renewals via ex parte despite having automated systems. The administrative burden on both staff and enrollees is likely to be higher in these states and they will likely face unique challenges as they work to complete the increased volume of renewals during the unwinding period.

Despite fairly broad adoption of the Medicaid expansion and 12-month postpartum coverage, only 14 states have adopted all three eligibility policies, which also includes 12-month continuous eligibility for all children. While these policies are not directly related to the ability to complete the renewal process, they do affect how frequently an enrollee may have their eligibility redetermined, and in the case of adoption of the Medicaid expansion, the likelihood that nonelderly adults will be able to retain coverage when their eligibility is redetermined during the unwinding period. All states will have to implement 12-month continuous eligibility for all children in both Medicaid and CHIP by January 1, 2024; however, currently, only 23 states have adopted this policy.

Implications

Unwinding the Medicaid continuous enrollment provision is expected to be challenging for all states, but state policy choices and system capacity will matter in terms of how many people are able to maintain Medicaid or transition to other types of coverage. This analysis offers one way to assess states on whether their approach to and capacity for processing renewals during the unwinding period are likely to lead to larger or smaller declines in Medicaid enrollment and can be useful for focusing monitoring efforts. However, state policies and procedures are likely evolving, and while this analysis examines state policies, how states implement those policies will be just as important a factor in how the unwinding proceeds across states. Implementation, in turn, will be affected by state staffing capacity, the effectiveness of state outreach to and communications with enrollees, and state engagement with key stakeholders, including MCOs, providers, and community organizations, to assist with enrollee outreach efforts.


~A.

Should I buy an electric vehicle? I’d say no

https://youtu.be/3BxB6vJA7Ok


~A.

Sunday, June 11, 2023

not the happpiest day

happy birthday to the 33 year old man that walked away.


